
| Verified against primary record | |
| Indexed definition | Replacing open invasive surgery with closed or localised technique, with the surgeon viewing the field indirectly[1] |
|---|---|
| Its two branches | Endoscopy and endovascular procedures. Robot-assisted surgery and microsurgery are not inside it[1] |
| Statistical treatment of invasiveness | No regulator defines the phrase; the United States procedure classification instead codes the approach on a dedicated axis[2] |
| Independently reported | |
| Fewer incisions, more harm | Single-incision gallbladder removal produced a doubled risk of severe adverse events across 46 randomised trials[3] |
| Bands apply only to the rows beneath them. The indexing vocabulary is a thesaurus for retrieving literature, not a regulatory instrument; it is cited here because no regulator defines the term. | |
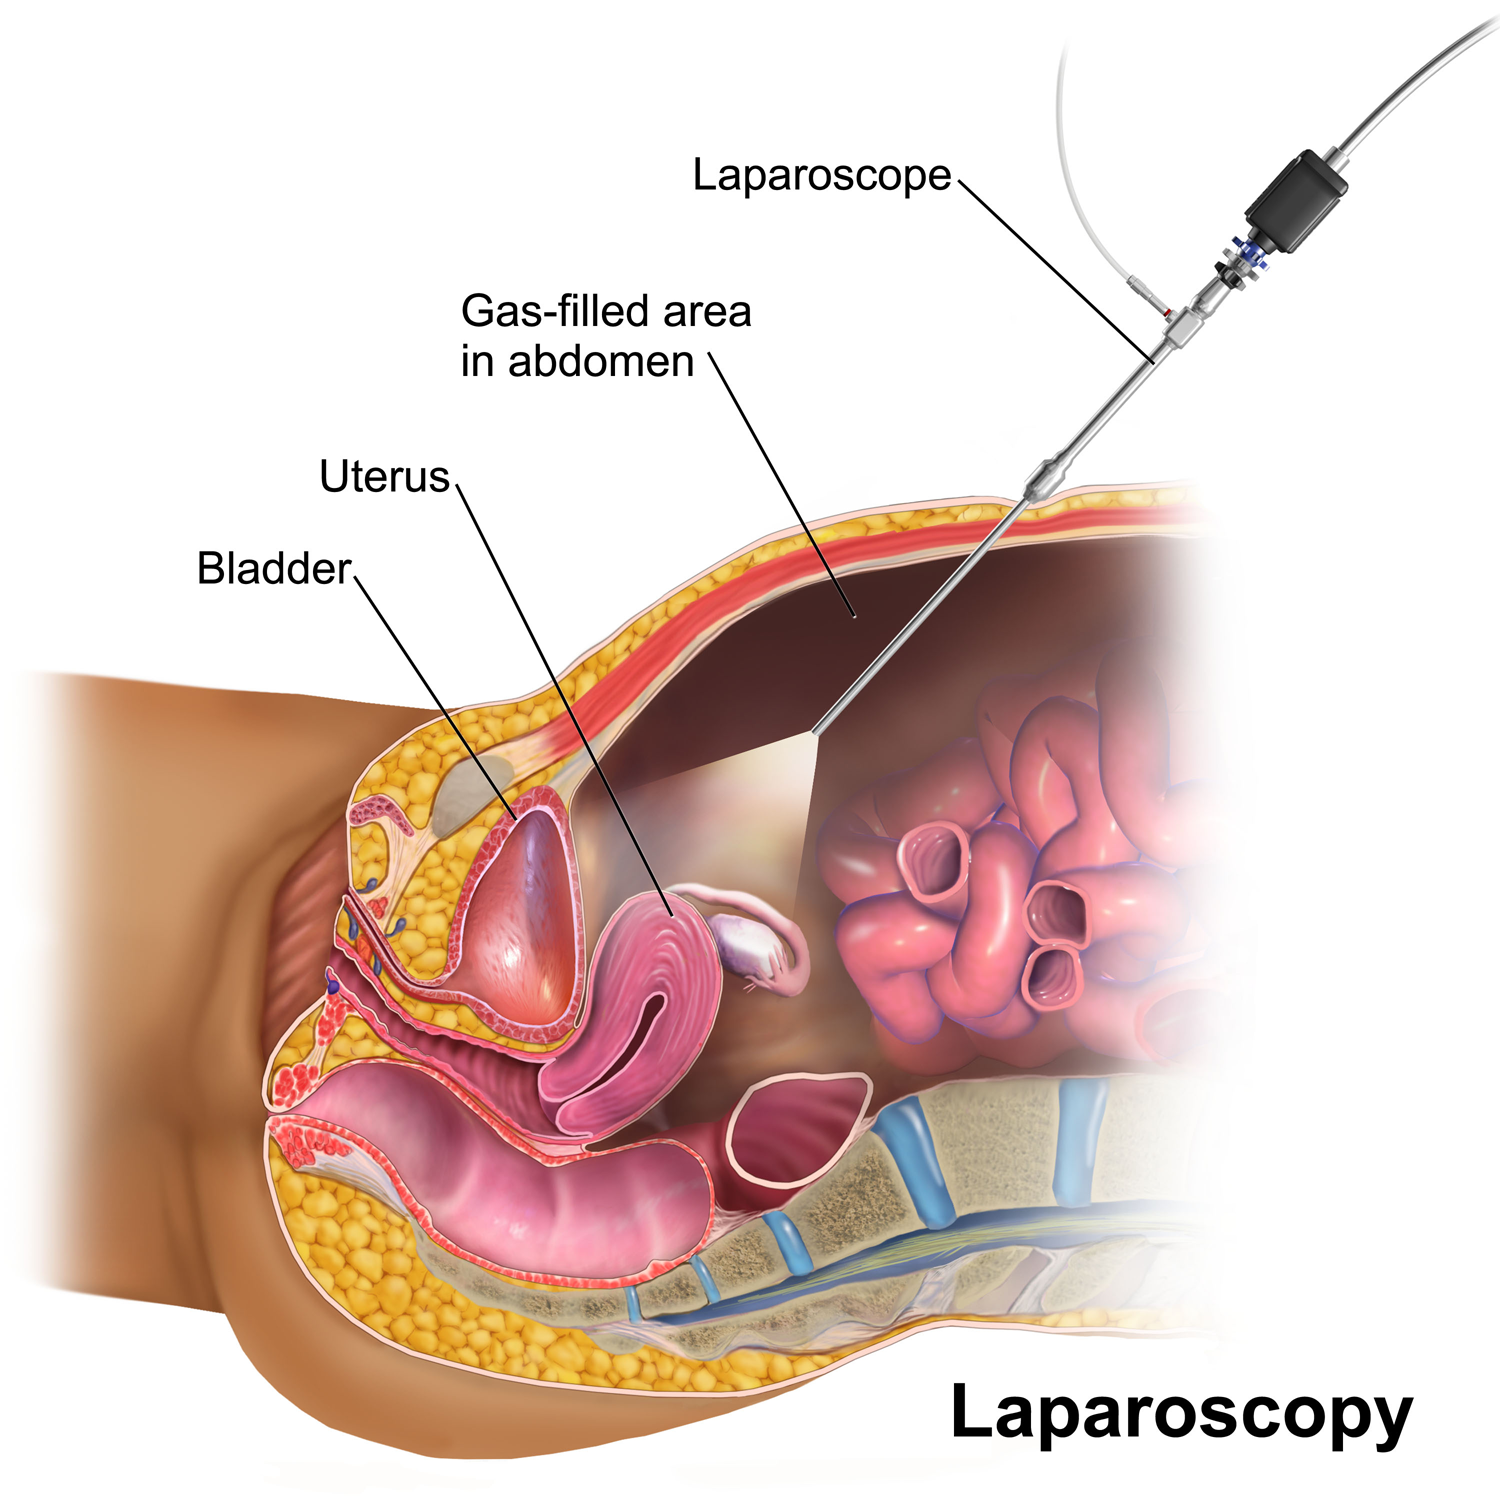
Minimally invasive surgery describes operations performed through small openings rather than a large incision, with the surgeon viewing the operative field indirectly. It describes access. It does not describe risk, and it is not the top of a ladder with robot-assisted surgery above it.
What the classification actually says
The only formal, maintained hierarchy covering these terms gives minimally invasive surgical procedures a single position in the operative tree, and defines the category as replacing open invasive surgery with closed or localised technique, typically using laparoscopic devices and remotely controlled instruments, with the surgeon viewing the field indirectly through an endoscope or similar device. It treats minimal access and minimally invasive as synonyms, listing both among its entry terms.[1] It has exactly two children: endoscopy, and endovascular procedures, defined as minimally invasive procedures performed inside blood vessels.[4][5] So the category is not only endoscopy: catheter-based work is its second branch.
Two terms often presented as advanced forms of minimally invasive surgery sit outside it. Robot-assisted surgery is classified under computer-assisted surgery, a separate branch of the operative tree, and is cross-listed under robotics in the technology tree. Microsurgery is a sibling of minimally invasive surgery rather than a part of it, and its second position is under micromanipulation, meaning it is classified by magnification rather than by access. Both points are covered in their own entries, and together they dispose of the ladder framing.
No regulator defines the phrase, but one classification codes the thing
Neither the procedure-coding guidelines nor the device regulator’s pages consulted define minimally invasive surgery. What exists instead is rigorous: the United States procedure classification devotes the fifth character of its seven-character codes to the approach, and seven approach values are in current use.[2] Several of its approach rules are more precise than the marketing vocabulary. Procedures within an orifice on structures visible without the aid of any instrumentation are coded as external, as are procedures applying external force through intervening layers. A laparoscopic-assisted open procedure is coded as open. A percutaneous endoscopic procedure that uses hand assistance, or an incision extension to remove a body part, remains percutaneous endoscopic. And conversion between approaches during an operation is coded as two procedures.[2]
The rule on laparoscopic-assisted procedures is worth isolating, because it cuts directly against a common marketing claim. In that classification an operation described as laparoscopic-assisted is formally an open operation.
It is audited as a quality measure
Minimally invasive access is a real audited metric rather than only a selling point. A national bowel cancer audit sets a contextual target that more than half of resections be performed by a minimally invasive approach, defining that as laparoscopic or robotic; 96 per cent of participating organisations met it, and in 2024 77 per cent of resections were minimally invasive, 55 per cent laparoscopic and 22 per cent robotic-assisted, up from 70 per cent minimally invasive in 2021.[6] Note that the audit folds laparoscopic and robotic together into one access category with a single target, which is the audit treating them as equivalent means to the same end rather than as successive rungs.
Cross-country comparison of such rates is unreliable, because reporting practice differs. One United States national statistical brief on hysterectomy trends does not break procedures down by approach at all, using a collapsed category that merges abdominal and vaginal routes, even though the underlying procedure classification codes the approach.[7] A minimally invasive rate from one country and another from a second country are frequently not the same measurement.
Minimally invasive does not mean lower risk
This is the claim most often made and least often supported. A meta-analysis of 46 randomised controlled trials found that reducing gallbladder removal to a single incision produced more harm, not less: overall adverse events at a relative risk of 1.41, severe adverse events at 2.06, incisional hernia at 2.97 and mild adverse events at 1.23, holding against both four-port and three-port comparators, with no deaths in either arm; the authors state that the consistent excess is grounds to reconsider the single-incision technique with current technology.[3] A national evidence summary gives the absolute rates: adverse events in 11.3 per cent of single-incision cases against 8.7 per cent of multi-incision cases, severe adverse events in 2.7 per cent against 1.1 per cent, with operating time about 17 minutes longer, against benefits of less pain and better cosmetic result and similar hospital stay and recovery.[8]
The device regulator has also recorded a signal in the other direction for one cancer indication, noting limited reports of lower long-term survival with minimally invasive cervical cancer surgery compared with open surgery.[9] The defensible summary is that minimally invasive describes access, not risk; that smaller access can increase technical difficulty and some harms; and that reducing incisions below the conventional number has been shown to make outcomes worse in at least one high-volume operation.
Why it matters for patients who must fly
Access route does change one thing that matters to a medical traveller, and it is not risk in general. Civil aviation guidance sets much shorter flight-deferral periods after laparoscopy than after open abdominal surgery, for a stated reason about trapped gas rather than about recovery or fitness. That material, and the important limits on how far it can be read, is set out in the entry on laparoscopic surgery.
See also
- Laparoscopic Surgery, the best-known form, and where the flight-timing guidance sits
- Endoscopic Surgery, the parent category of laparoscopy within this one
- Robot-Assisted Surgery, classified as a control modality rather than an access modality
- Microsurgery, defined by magnification and routinely performed through open incisions
References
- United States National Library of Medicine. Medical Subject Headings descriptor Minimally Invasive Surgical Procedures (D019060). Introduced 1996, last revised 27 May 2020. Verified against primary record: the descriptor record was opened and its scope note, single tree number and entry terms read, and its children identified from the tree. Retrieved 10 October 2026.
- Centers for Medicare and Medicaid Services. ICD-10-PCS Official Guidelines for Coding and Reporting 2027. Verified against primary record: the guidelines were opened and the conventions establishing the approach axis and the number of approach values read, together with the rules on external approach, laparoscopic-assisted procedures, hand assistance and conversion between approaches. The guidelines do not use the phrase minimally invasive. Retrieved 10 October 2026.
- Arezzo A, Passera R, Forcignano E, Rapetti L, Cirocchi R, Morino M. Single-incision laparoscopic cholecystectomy is responsible for increased adverse events: results of a meta-analysis of randomized controlled trials. Surgical Endoscopy 2018;32:3739-3753, online 9 March 2018. Verified against primary record: the article was opened and the relative risks, the comparator analyses and the authors’ conclusion read. Retrieved 10 October 2026.
- United States National Library of Medicine. Medical Subject Headings descriptor Endoscopy (D004724). Introduced 1966, last revised 25 June 2010. Verified against primary record: the descriptor record was opened and its two tree positions read, establishing it as a child of minimally invasive surgical procedures. Retrieved 10 October 2026.
- United States National Library of Medicine. Medical Subject Headings descriptor Endovascular Procedures (D057510). Introduced 2011. Verified against primary record: the descriptor record was opened and its scope note and tree position read, establishing it as the second child of minimally invasive surgical procedures. Retrieved 10 October 2026.
- Healthcare Quality Improvement Partnership, National Cancer Audit Collaborating Centre and Royal College of Surgeons of England. Bowel cancer: State of the Nation Report 2026, National Bowel Cancer Audit. Published 8 October 2026. Verified against primary record: the report was opened and the minimally invasive target, its definition, the proportion of organisations meeting it and the 2024 and 2021 proportions read. The report’s denominator wording is inconsistent between its text and the cited figure, and no case count is given for the 2024 proportion. Retrieved 10 October 2026.
- Agency for Healthcare Research and Quality, Healthcare Cost and Utilization Project. Trends in hysterectomies and oophorectomies in hospital inpatient and ambulatory settings, 2005-2013. Statistical Brief 214, November 2016. Verified against primary record: the brief was opened and its case definition inspected, establishing that it does not break procedures down by approach. Retrieved 10 October 2026.
- National Institute for Health and Care Research. Gallbladder surgery through a single-incision is more risky than a multiple incision technique. 17 July 2018. Verified against primary record: the summary was opened and the absolute event rates, the operating-time difference and the reported benefits read. The page carries a notice that it is more than five years old. Retrieved 10 October 2026.
- United States Food and Drug Administration. Computer-assisted surgical systems. Page published and last modified 24 September 2026. Verified against primary record: the page was opened and its note on reports of lower long-term survival with minimally invasive cervical cancer surgery read. Retrieved 10 October 2026.
Sourcing note: no professional society taxonomy was located that defines or competes with the indexing hierarchy used here, so the boundaries in this entry are attributed to that vocabulary and to the procedure classification rather than to surgeons collectively. The full list of approach values in the procedure classification was not verified from a current source and is therefore not reproduced; only the number of values in current use and the specific rules quoted above were read from the 2027 guidelines. Whether that classification records robotic assistance separately from approach was not established and is not asserted.